
Everything You Need to Know About Adrenal Gland Surgery
Authored by:
Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)
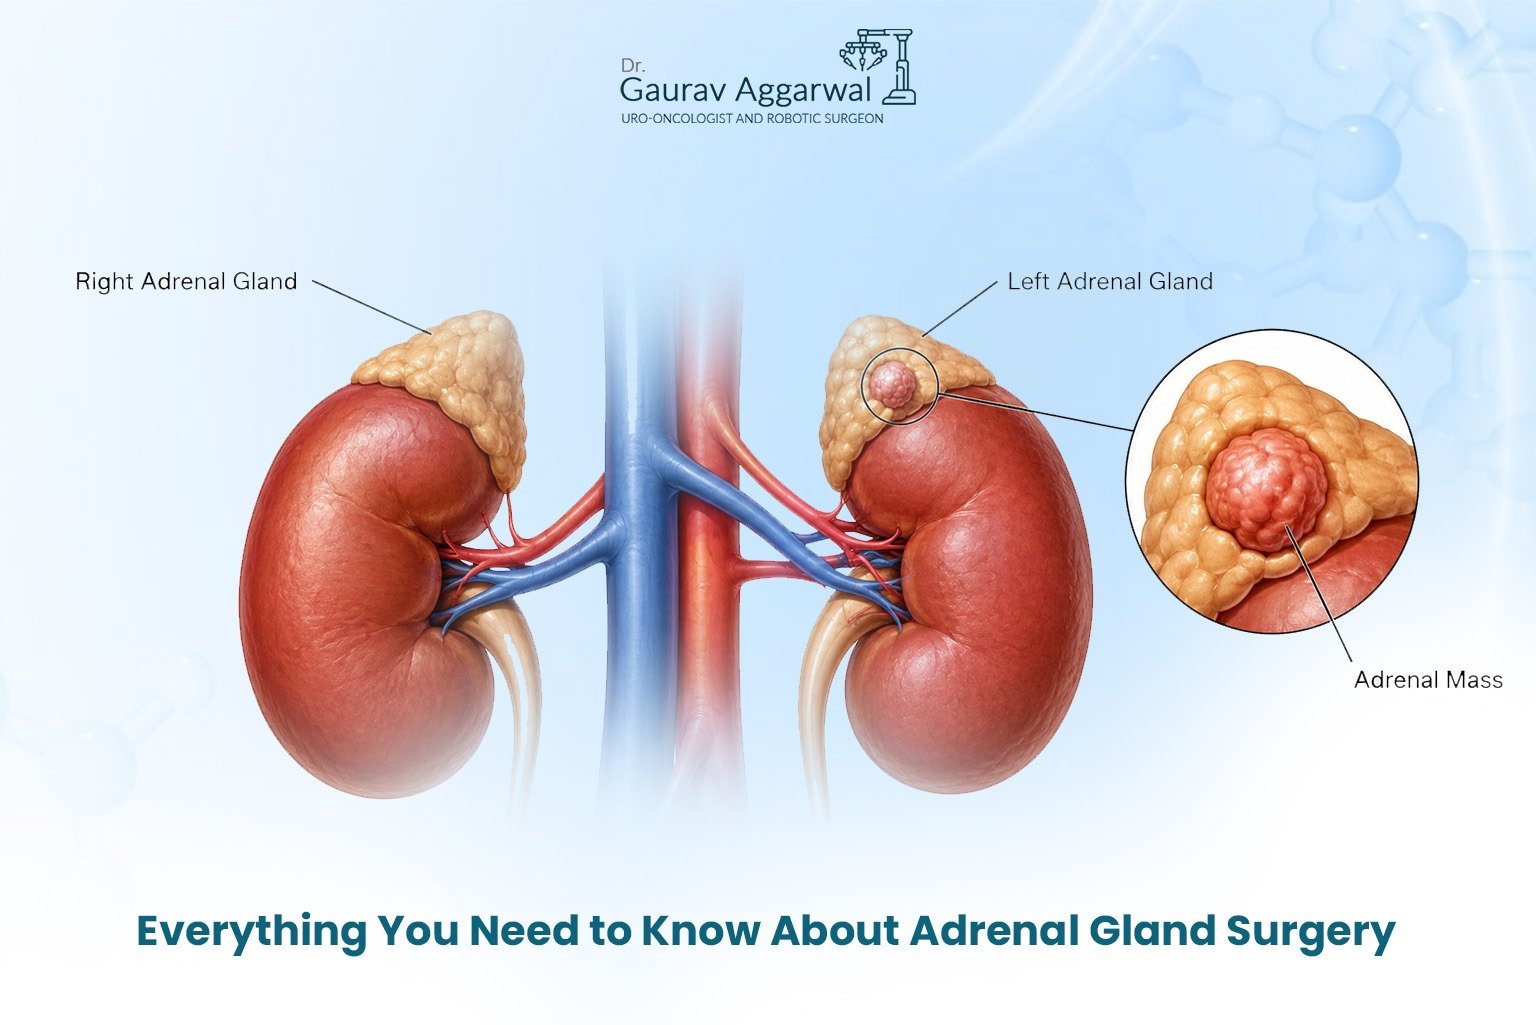
Adrenal gland surgery can sound intimidating, especially when it is being discussed as part of cancer treatment. Understanding what the surgery involves and what recovery looks like can make the process more manageable. The adrenal glands are small hormone-producing organs located above the kidneys, but they have an important role in regulating blood pressure, metabolism, and the body’s response to stress.
Adrenal cancer is rare, and treatment needs to be planned carefully based on the size and location of the tumour, whether it produces hormones, whether it has spread, and the patient’s overall health. For patients exploring adrenal cancer treatment in Newtown, surgery is often the main curative option when the disease is localised.
Understanding Adrenal Gland Cancer
Adrenal cancer, also known as adrenocortical carcinoma (ACC), develops from malignant cells in the adrenal cortex. It accounts for approximately 0.05-0.2% of all cancer diagnoses, making it an uncommon condition that requires specialised evaluation and surgical expertise.
Not every adrenal tumour behaves in the same way. Some tumours are functional, meaning they produce excessive hormones, while others are non-functional and may not cause hormone-related symptoms.
Important factors doctors consider include:
- Tumour size and growth
- Whether the tumour has invaded nearby tissues
- Lymph node involvement
- Spread to distant organs
- Hormone production
- The patient’s age and overall health
- Possible inherited cancer syndromes
Because adrenal tumours can sometimes resemble benign growths, diagnosis usually involves a combination of hormonal testing and detailed imaging. In selected cases, a biopsy may also be considered.
What Symptoms Can Adrenal Cancer Cause?
Adrenal cancer can present differently from one person to another. Some patients experience hormone-related symptoms, while others may have more general symptoms or discover the tumour accidentally during imaging for another health concern.
Hormone-related symptoms can include:
- High blood pressure and low potassium levels
- Changes caused by excess cortisol
- Virilization or feminization due to abnormal sex hormone production
- Central weight gain, muscle weakness, skin striae, or glucose intolerance
- Mood or psychiatric changes associated with hormonal excess
Other possible symptoms include:
- Abdominal or flank pain
- A palpable abdominal mass in larger tumours
- Fatigue
- Unexplained weight loss
- Loss of appetite
Sometimes, adrenal cancer is found incidentally during a scan performed for an unrelated reason.
How Is Adrenal Cancer Diagnosed?
A detailed diagnostic assessment helps the medical team understand exactly what they are dealing with before surgery is planned.
The evaluation may include:
- Hormonal assessment, including 24-hour urine cortisol, plasma ACTH, aldosterone-renin ratio, and androgen levels
- CT scans using a fine-cut protocol
- MRI to assess tumour size, characteristics, invasion, and possible spread
- Biopsy when imaging does not provide a clear diagnosis
- Chest and abdominal imaging, and sometimes PET-CT, for staging
- Genetic evaluation in selected patients with a possible hereditary risk
This information helps the team plan surgery with the goal of complete tumour removal while protecting surrounding structures.
Surgical Approaches to Adrenal Cancer Treatment in Newtown
For localised adrenal cancer, adrenalectomy, or surgical removal of the affected adrenal gland, is generally the primary curative approach. The aim is complete tumour removal with negative surgical margins.
Depending on the tumour and the patient’s condition, the surgeon may recommend one of several approaches.
Robotic-Assisted Adrenalectomy
Robotic surgery has become an important option in selected adrenal cases. It uses a high-definition camera and specialised instruments that allow the surgeon to work with enhanced visualisation and precision.
Potential advantages can include:
- Magnified visualization of delicate adrenal structures
- Greater instrument stability and tremor filtering
- Small port incisions and reduced surgical trauma
- Less postoperative pain in suitable cases
- Faster recovery and shorter hospital stays
- Better access in anatomically complex situations
Robotic techniques may help in complex cases, but tumour characteristics and oncological safety remain the priority.
Open Adrenalectomy
An open approach provides broad access to the tumour and surrounding anatomy. It may be recommended when a tumour is very large, involves major blood vessels, or cannot be safely removed using minimally invasive techniques.
Open surgery can also allow en bloc removal of nearby organs if the tumour has invaded them and complete cancer removal requires it. The trade-off is generally a longer hospital stay and recovery period.
Laparoscopic Adrenalectomy
Laparoscopic surgery uses small incisions and specialised instruments. It can reduce surgical trauma and support quicker recovery in appropriately selected patients. However, it is generally more suitable for smaller tumours without extensive vascular involvement, and the technical demands can be significant.
The final surgical decision depends on the tumour, the patient’s physiology, the extent of disease, and the surgeon’s expertise. In cancer surgery, achieving safe and complete tumour removal is more important than choosing a particular technology.
Preparing for Surgery
Good preparation is especially important when the tumour produces hormones.
Before surgery, the medical team may focus on:
- Controlling excess hormone production
- Correcting low potassium levels
- Assessing blood pressure and other metabolic changes
- Planning specialized anesthesia
- Reviewing imaging to understand blood vessels and nearby organs
- Planning lymph node management when clinically indicated
During surgery, careful haemodynamic monitoring is important because manipulating a hormone-producing tumour can sometimes trigger sudden hormone release. Meticulous dissection also helps reduce the risk of tumour spillage and injury to surrounding structures.
Adrenal surgery is often a multidisciplinary process involving urologists, oncologists, anaesthesiologists, radiologists, and pathologists. This coordinated approach helps ensure that diagnosis, surgery, and postoperative care work together rather than functioning as separate steps.
Recovery After Adrenal Surgery
Recovery after adrenal cancer treatment in Newtown depends on the surgical approach, tumour characteristics, and the individual’s overall condition.
For minimally invasive procedures, the hospital stay is typically around 1-3 days, while open surgery may require approximately 3-5 days. Pain is usually managed using a multimodal approach, with the aim of providing effective relief while limiting unnecessary opioid use.
Patients are generally encouraged to gradually increase activity. A return to normal activities may take around 4-6 weeks, while strenuous activity is restricted initially to allow proper healing.
Hormone replacement depends on how much adrenal tissue remains. After removal of one adrenal gland, hormone replacement is rarely required. If both adrenal glands are removed, permanent glucocorticoid and mineralocorticoid replacement is necessary.
Follow-up remains an important part of recovery. It may include:
- Imaging surveillance
- Hormonal reassessment
- Tumour marker monitoring
- Checking for recurrence
- Reviewing whether additional chemotherapy or radiation is appropriate
Understanding Pheochromocytoma
Pheochromocytoma is a rare adrenal tumour that develops from the hormone-producing cells of the adrenal medulla. Unlike adrenocortical carcinoma, which develops in the adrenal cortex, pheochromocytoma can produce excessive amounts of catecholamines such as adrenaline and noradrenaline.
These tumours may cause episodes of high blood pressure, headaches, excessive sweating, palpitations, tremors, and a rapid heartbeat. However, some patients may have few or no noticeable symptoms, and the tumour may be discovered incidentally during imaging.
Diagnosis usually involves biochemical testing, including plasma or urine metanephrines, followed by imaging such as CT or MRI to locate the tumour and assess its characteristics. Genetic testing may also be considered because pheochromocytoma can be associated with inherited conditions.
Surgery for Pheochromocytoma
Surgery is the main treatment for a localised pheochromocytoma. However, careful preparation is essential because manipulating a hormone-producing tumour can cause sudden changes in blood pressure and heart rate.
Before surgery, patients may receive medication to control blood pressure and reduce the effects of excess catecholamines. During surgery, specialised anaesthetic monitoring and careful tumour handling are important to maintain cardiovascular stability.
Depending on the tumour’s size, location, and characteristics, adrenalectomy may be performed using a robotic, laparoscopic, or open approach. The choice of technique is individualised, with surgical safety and complete tumour removal remaining the primary goals.
Because pheochromocytoma can be associated with hereditary syndromes and may occur in both adrenal glands, selected patients may also require genetic evaluation and long-term follow-up.
Why Advanced Surgical Techniques Matter
Modern adrenal surgery has continued to evolve, particularly for complex tumours. In selected cases, advanced techniques may include en bloc resection of involved organs, vascular reconstruction, intraoperative ultrasound, and frozen-section assessment.
These techniques are used when clinically appropriate and can help surgeons understand tumour extent, manage involved structures, and work toward complete cancer removal. Robotic modifications can also provide greater control when operating around small, delicate structures.
The goal is to select the safest, most effective technique for the individual patient while maintaining sound oncological principles.
Dr Gaurav Aggarwal: Specialized Care for Adrenal Tumours
Dr Gaurav Aggarwal is a fellowship-trained uro-oncologist and robotic surgeon with expertise in complex urological and adrenal cancers. His approach combines surgical precision with an understanding of the wider oncological needs of each patient.
His experience includes:
- Robotic surgery, with 1,500+ documented robotic procedures
- Complex adrenal cancers involving nearby organs
- Multivisceral and en bloc resection
- Uro-oncology involving prostate, kidney, bladder, penile, testicular, and adrenal cancers
- Individualized surgical planning based on tumour and patient factors
- Coordination with medical oncologists, radiologists, and anesthesiologists
- Evidence-based surgical practice and continued focus on innovation
For patients considering adrenal cancer treatment in Newtown, having a specialist who can evaluate both the tumour and the broader treatment plan can be an important part of making an informed decision.
FAQ
-
What is the survival rate for adrenal cancer?
Five-year survival rates range from 35 to 50% for localised disease. Outcomes depend on stage, completeness of tumour removal, and postoperative treatment.
-
Will I need hormone replacement after adrenalectomy?
Usually not after removal of one adrenal gland. Bilateral adrenalectomy requires permanent glucocorticoid and mineralocorticoid replacement.
-
How long does recovery take after robotic adrenalectomy?
Many patients can return to light activities within 2-3 weeks, while full recovery and strenuous activity may take around 6-8 weeks.
-
Can large adrenal tumours be treated robotically or laparoscopically?
Some can, but very large tumours or those with significant vascular invasion may require open surgery for better oncological control.
-
Is pheochromocytoma treated with surgery?
For a localised pheochromocytoma, surgery is generally the main treatment. Because these tumours can release excess hormones, careful medical and anaesthetic preparation is important before adrenalectomy.
