Dr. Gaurav Aggarwal | Uro-Oncologist in Kolkata

Blog

Your blog category

Advanced radiotherapy equipment used for prostate cancer treatment without surgery in a modern cancer treatment facility.

Can Prostate Cancer Be Treated Without Surgery? Understanding Your Options

Can Prostate Cancer Be Treated Without Surgery? Understanding Your Options Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  After a prostate cancer diagnosis, patients often ask the same first question: do I really need an operation? For many men, the answer is not right away, and sometimes not at all. Prostate cancer treatment without surgery is a well-established approach that, in carefully selected cases, can offer excellent long-term control. A good treatment plan starts with understanding the available options, how each one works, and which one best suits your specific condition. This guide walks through those options in plain language. Why Surgery Is Not Always the First Step Surgery, usually a radical prostatectomy, removes the entire prostate gland. It works well for many men whose cancer is confined to the gland, and it remains a strong option. Still, it is not automatically the first move. The right prostate cancer treatment depends on several factors: The Gleason score describes how aggressive the cancer cells look under the microscope. The PSA level at diagnosis gives a rough sense of how much disease may be present. The clinical stage shows whether the cancer is still inside the prostate or has spread beyond it. Your age, general health, and life expectancy affect how much a given treatment is likely to help. Your priorities around urinary control, sexual function, and recovery time matter as much as the numbers. Active Surveillance: Watching Before Acting For low-risk cancers, many urologists suggest active surveillance rather than immediate treatment. The aim is to avoid treating a cancer that may never cause harm, while staying ready to act if it changes. Active surveillance is a valid prostate cancer treatment strategy, not a form of neglect. Monitoring usually includes: PSA blood tests every few months during the first years. Periodic MRI scans to track any change in the tumour. Follow-up biopsies at planned intervals, guided by the results of earlier tests. Many men on surveillance never need active treatment. Those who do can still access the full range of options later, so starting with monitoring rarely closes any doors. Regular check-ins also give you a clear reason to raise concerns early instead of waiting for symptoms. Radiation Therapy Radiation is a central part of prostate cancer treatment for disease that is still localised to the gland. Modern machines deliver high doses with far more precision than older methods, which helps protect the bladder and rectum. Your radiation oncologist will plan the dose and schedule around your specific tumour. The main approaches include: External beam radiotherapy sends radiation from a machine outside the body, usually over several weeks of daily sessions. Stereotactic body radiotherapy, often called SBRT, delivers higher doses in fewer sessions, with careful targeting. Brachytherapy places radioactive seeds inside the prostate and suits selected low and intermediate-risk patients. Side effects can include urinary frequency, a mild burning sensation during urination, bowel irritation, and tiredness. Most settle within weeks to months after treatment ends. Erectile function may change over time, so it is worth raising this early with your doctor, since several strategies can help. Hormone Therapy and Its Role Prostate cancer cells often rely on androgens, the male hormones such as testosterone, to grow. Androgen deprivation therapy, usually called ADT, lowers these hormone levels or blocks their effect. Hormone therapy is a key prostate cancer treatment in a few situations: On its own, for men who cannot have or do not want other treatments. Alongside radiation, for higher-risk diseases where combining the two improves outcomes. Later on, when the cancer returns after earlier treatment. Common side effects include hot flushes, reduced libido, fatigue, weight gain, and loss of muscle mass. Many of these respond well to regular exercise, dietary changes, and medicine. They should not become a reason to stop treatment without speaking to your doctor first. Systemic and Targeted Options When cancer spreads or stops responding to hormone therapy, the focus shifts to medicines that act throughout the body. Advanced prostate cancer treatment often combines several of these approaches. Your doctor may discuss: Chemotherapy, most often docetaxel, for disease that has progressed. PARP inhibitors, a targeted group of drugs considered for men whose tumours carry changes in genes such as BRCA1 or BRCA2. Certain immunotherapy options for selected patients. Genetic testing, usually done with a blood or tumour sample, helps identify which targeted options may apply. Clinical trials also test newer treatments, so ask whether one could suit your situation. Focal Therapy: A Newer Middle Ground Focal therapy is a newer prostate cancer treatment approach that targets only the part of the gland containing the tumour. Methods such as cryotherapy or high-intensity focused ultrasound aim to control the cancer while sparing the rest of the prostate. It is offered in carefully selected cases, but long-term data are still building compared with surgery and radiation. Treat it as a topic for a specialist consultation rather than a simple shortcut. Lifestyle and Supportive Care Supportive care is an important part of prostate cancer treatment, even when the medical plan is clear. Daily habits can make a real difference to energy, mood, and recovery: Pelvic floor exercises, sometimes called Kegels, can support bladder control after treatment when done correctly. Regular walking or strength training helps counter fatigue and muscle loss during hormone therapy. A diet rich in vegetables, pulses, whole grains, and lean protein supports overall health throughout treatment. Emotional well-being matters too. Many men find that counselling, support groups, or open conversations with family ease the strain of a diagnosis. Asking for help is part of good care, not a sign of weakness. How to Choose the Right Path Good decisions come from good questions. Bring the following to your next appointment: Ask for your exact risk group and what it means in practical terms. Ask which options are standard care and which are still experimental. Ask how each option may affect continence and sexual function and for how long. Ask how many appointments and sessions each option will

Can Prostate Cancer Be Treated Without Surgery? Understanding Your Options Read More »

The future of urology with AI-powered technology, robotic surgery, and a digital illustration of the urinary system for advanced patient care.

The Future of Urology: How AI and New Tools May Change Patient Care

The Future of Urology: How AI and New Tools May Change Patient Care Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  Not long ago, a kidney tumour was usually found when it had already grown large enough to cause pain or bleeding. Today many are picked up by accident, on a scan done for something unrelated, and removed through a few small keyhole cuts. That one change says a lot about where this field is heading. This blog looks at the future of urology: which tools are already in clinics, which ones are still being tested, and what they mean for a patient sitting in a waiting room in Kolkata today. What Urology Already Looks Like Now Before looking ahead, it helps to see how much has already moved. Some things that were rare a decade ago are now routine in good centres: MRI of the prostate before a biopsy, so the needle goes to the suspicious spot instead of being placed blindly Flexible cystoscopes with sharper cameras, which show bladder tumours that older scopes could miss PSMA scans that show where prostate cancer has spread, if it has Laser techniques for stones and prostate enlargement Laparoscopic and robotic operations for kidney, bladder and prostate cancers None of this is science fiction. What’s coming next builds on these tools rather than replacing them. Robotic Surgery: Where It Stands Robotic surgery in urology has grown fast because the pelvis and the kidney are tight, deep spaces. Straight laparoscopic instruments struggle there. A robotic system gives the surgeon a magnified 3D view and instruments that bend like a wrist, which makes fine work possible, such as sparing the nerves around the prostate or stitching the kidney after a tumour is removed. What patients usually notice is the recovery. Smaller cuts, less blood loss, a shorter hospital stay and an earlier return to normal walking. Two things are worth saying plainly, though. The robot doesn’t operate on its own. The surgeon controls every movement, so experience matters more than the machine. And robotic systems, including ones now built in India, are becoming easier to find outside the big metros. That should widen access, but a newer hospital room doesn’t automatically mean a better operation. For a patient, the practical questions are simple: does this operation suit my tumour, and does my surgeon do it often? Software That Learns From Scans: Promising, Still Maturing The most talked-about change is software that learns from thousands of images. Here’s where it’s being tested or has started to appear: Reading prostate MRI scans and marking areas that look suspicious, so the radiologist and surgeon can double-check them. Watching live cystoscopy video and flagging patches of the bladder lining that might be tumours. Helping pathologists scan biopsy slides faster and more consistently. Estimating which cancers are likely to return, so follow-up can be planned more carefully. Sorting through long medical records so doctors spend less time on paperwork. AI in urology works best as a second pair of eyes. It’s good at catching patterns in huge volumes of images. It isn’t good at weighing your age, your other illnesses and your family’s wishes. That part stays with the doctor. There’s another honest limit. Many of these tools were trained on data from other countries. They need to be tested on Indian patients, with Indian scan machines, before anyone should trust them blindly. New Tests and Treatments Worth Watching Beyond AI and robots, a quieter group of developments may shape the future of urology just as much: Urine and blood tests that pick up traces of bladder or prostate cancer, which could cut down on repeat invasive checks Genetic and molecular testing of tumours, so medicines can be matched to the cancer instead of used by guesswork 3D models built from a patient’s own scan, which let a surgeon rehearse a complex kidney operation before entering the theatre Targeted treatments that treat only the cancerous part of an organ in selected cases Video consultations for follow-up, which spare patients from districts a long train ride for a ten-minute review That last one deserves attention. For many families outside Kolkata, the biggest barrier to cancer care is travel. Reviewing a scan or a blood report over a video call won’t replace the first visit, but it can make later ones lighter. Recovery Is Changing Too Surgery is only part of the story. Hospitals are rethinking what happens before and after the operation: Getting up and walking early, sometimes the same evening, because lying in bed slows healing Simple exercises and breathing practice before surgery, so the body goes in stronger Pain control that depends less on strong painkillers Phone or video check-ins in the first weeks, so a worrying symptom gets noticed early Clear written instructions for the family on what is normal and what needs a call None of this sounds dramatic. Together it means fewer complications and a faster return to work, home and routine, which is what most patients care about once the operation is over. What This Could Mean for You as a Patient Put together, the future of urology points toward a few clear gains: Cancers found earlier, when they’re smaller and easier to treat Fewer biopsies done blindly or unnecessarily Operations through smaller cuts, with quicker recovery Treatment choices matched more closely to the individual tumour Follow-up that fits around your life instead of controlling it Some things won’t change, and it’s worth saying them out loud. Blood in the urine still needs tests the same week. A rising PSA still needs a proper explanation. A good conversation with your surgeon still counts for more than any brochure. Questions to Ask Before Accepting Any New Technology New doesn’t always mean better for your case. Before agreeing to a newer scan, test or operation, ask: What will this change about my treatment? Is it proven for my type of cancer, or is it still being studied? What are the standard options, and why

The Future of Urology: How AI and New Tools May Change Patient Care Read More »

PSA test for prostate cancer showing a blood test used to check PSA levels, detect prostate health issues and assess cancer risk in men.

A Beginner’s Guide to PSA Tests and Prostate Health

A Beginner’s Guide to PSA Tests and Prostate Health Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  Ask a few men over fifty about their prostate and you’ll get a shrug, a joke, or a quick change of subject. Then a relative gets diagnosed and suddenly everyone wants to know what a PSA number means. It helps to understand the basics before that day comes. This guide covers what the prostate does, what a PSA test measures, who should think about getting one, how to prepare, and what to do when a result comes back high. No jargon and no scare tactics, just enough to have a sensible conversation with your doctor. What Is the Prostate and Why Does It Matter? The prostate is a small gland, roughly the size of a walnut, that sits just below the bladder and wraps around the urethra. Its job is to make the fluid that carries sperm. The position is the whole story. Because the gland surrounds the urethra, any growth in it can squeeze the urinary passage. And because it sits deep in the pelvis, early problems rarely announce themselves. Most men get three kinds of prostate trouble as they age: Benign enlargement: the gland grows larger with age and slows the urine stream. It’s not cancer. Prostatitis: swelling or infection that causes pain, burning or fever. Prostate cancer: abnormal cells that grow out of control, often slowly, but not always. What Is PSA? PSA stands for prostate-specific antigen. It’s a protein made by the prostate, and a small amount always leaks into the blood. A PSA blood test measures that amount in nanograms per millilitre. Here’s the catch. PSA is specific to the prostate, not to cancer. Anything that irritates or enlarges the gland can push the number up. That’s why one reading never tells the full story. Why Do Doctors Order a PSA Test? There are three main reasons: Screening: checking men with no symptoms so a problem can be caught early Investigation: working out the cause of urinary symptoms or an abnormal finding on examination Monitoring: tracking PSA after prostate cancer treatment to see whether the disease is staying away A PSA test for prostate cancer works best as one piece of a bigger picture. Doctors combine it with your age, family history, a physical examination and, when needed, an MRI scan before deciding anything. Who Should Consider Getting Tested? There’s no single rule, but these are common starting points: Men around 50 can have a conversation with their doctor about screening Men with a father or brother who had prostate cancer should start earlier, often around 45 Men with two or more close relatives affected may be advised to start earlier still Men with urinary symptoms at any age should get checked rather than wait Notice the word “conversation”. Screening is a decision made with your doctor, after weighing benefits and limits. It isn’t an automatic yes for everyone. Symptoms Worth Reporting Early prostate cancer usually causes nothing you can feel. When symptoms do show up, they often overlap with harmless enlargement, so don’t self-diagnose. See a doctor if you notice: A weak or slow urine stream Needing to pass urine several times at night A sudden, urgent need to go Difficulty starting, or stopping and starting Blood in urine or semen Persistent pain in the lower back, hips or pelvis Blood in urine deserves a prompt visit, whatever your age. How to Prepare for the Test A PSA test needs no fasting, but a few things can throw the number off. Plan around them: Avoid ejaculation for 24 to 48 hours before the blood draw Skip long cycling sessions for two days, since pressure on the prostate can raise PSA Postpone the test if you’ve had a urine infection or a catheter recently Tell your doctor about every medicine you take, because some prostate medicines can nearly halve the PSA value Mention any recent prostate examination or procedure The blood draw itself takes a minute. Results usually arrive within a day or two. Understanding Your Result Many labs flag anything above 4 ng/mL, but that line isn’t a verdict. Normal values rise slowly with age, and the right cut-off for a 45-year-old is lower than for a 70-year-old. Doctors also look at how fast the number is climbing between two readings. Methods vary slightly between labs, so keep your old reports and compare like with like. Roughly, here’s how to think about it: Low and stable: usually reassuring. Your doctor will suggest when to repeat it. Mildly raised: often repeated after a few weeks, once any infection or other trigger is ruled out. Clearly raised or rising fast: needs a closer look, usually starting with an MRI of the prostate. Why a High PSA Doesn’t Always Mean Cancer This is the part that causes the most panic, so read it twice. A high reading can come from: An enlarged prostate Prostatitis or a urine infection Recent ejaculation or cycling A catheter or a recent procedure Simply getting older Most men with a raised PSA turn out not to have cancer. The number is a reason to look further, not a reason to assume the worst. What Happens After an Abnormal Result? Your doctor will usually go step by step, and not every step is needed for everyone: Repeat the test after a few weeks Check related measures, such as free PSA or PSA density, which help separate cancer from enlargement Do an MRI scan of the prostate to look for suspicious areas Advise a biopsy only if the scan or the numbers point that way A biopsy is the only way to confirm cancer. It’s recommended when earlier steps raise real suspicion, not as the first move. The Limits of PSA Screening An honest guide should say this plainly. A PSA test for prostate cancer isn’t perfect. It can miss a cancer, and it can flag one that would never have caused harm. Some prostate

A Beginner’s Guide to PSA Tests and Prostate Health Read More »

Cystoscopy procedure explained by a urologist using a medical screen to discuss bladder examination, diagnosis, and recovery.

Cystoscopy Explained: Why It’s Done and What Recovery Is Like

Cystoscopy Explained: Why It’s Done and What Recovery Is Like Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  Blood in your urine is one of those symptoms people try to ignore. So is a burning that won’t go away, or a bladder that never feels fully empty. If it keeps happening, the next step is often a quick look inside the bladder with a thin camera. That test is called a cystoscopy, and just hearing the name makes many patients tense up. Most of the fear comes from not knowing what happens in the room. This guide walks you through the cystoscopy procedure from start to finish: why we recommend it, what you’ll feel, how recovery goes, and which symptoms mean you should call us. What a Cystoscopy! Actually, it is A cystoscope is a thin tube with a light and a tiny camera at its tip. It enters through the urethra; the channel urine passes through and moves into the bladder. The picture appears on a monitor, so we can see the bladder lining live instead of guessing from a scan. There are two kinds: Flexible cystoscope: bends as it moves, so it’s gentler. Most check-ups use this one, in the clinic, with numbing gel. Rigid cystoscope: a straighter, firmer scope. We use it when a larger biopsy or a treatment is needed, usually under anaesthesia. Why Doctors Recommend It Scans are useful, but they can miss small or flat changes in the bladder wall. A camera doesn’t. We suggest a cystoscopy for: Blood in the urine, even if it happened once and didn’t hurt Urinary infections that keep coming back after treatment Burning, urgency or frequent urination that won’t settle A shadow or thickening on an ultrasound or CT scan Bladder stones A narrowed urethra (stricture) that weakens the stream Checking or removing a ureteric stent Regular follow-up after bladder cancer treatment For a uro-oncology surgeon like Dr Gaurav Aggarwal, bladder cancer is the diagnosis that matters most here. Painless blood in the urine is its most common early sign, and a cystoscopy is how we confirm or rule it out. Early tumours are often removed through the scope itself, without a large cut. Who Shouldn’t Wait Some people carry a higher risk of bladder problems, and for them a symptom is never “probably nothing.” Come in sooner if you: Smoke, or used to. Smoking is the biggest known risk factor for bladder cancer Are above 50 and have noticed any blood in your urine Have worked for years around dyes, paints, leather, rubber or industrial chemicals, which is common in Kolkata’s textile and manufacturing units Had radiation to the pelvis in the past Have a close relative who had bladder or kidney cancer A single episode of bloody urine that clears on its own still deserves a check. The bleeding from a bladder tumour often stops and starts, which is exactly why people relax and then lose months. If you experience persistent urinary symptoms or blood in your urine, consulting a qualified urologist in Kolkata can help determine whether a cystoscopy is necessary. How to Prepare Preparation is simple. Tell us about every medicine you take, especially blood thinners and aspirin Give a urine sample first. If there’s an infection, we treat it and postpone the test For a clinic check, you can usually eat and drink normally If you’re having anaesthesia, you’ll be told how many hours to fast Empty your bladder just before you go in Bring a family member if sedation is planned, since you shouldn’t drive afterwards What Happens During the Test The cystoscopy procedure takes about 5 to 10 minutes for a routine check. A biopsy or treatment takes longer. The usual order goes like this: You lie on your back with your knees apart The area is cleaned and numbing gel goes into the urethra. We wait a few minutes for it to work The scope slides in gently, and sterile fluid fills the bladder so the lining opens out and is easier to see You’ll feel pressure and an urge to urinate. That’s the fluid, and it’s normal We examine the whole bladder wall and the opening of the urethra. In men, we also see the prostate section of the urethra If anything looks unusual, a small tissue sample is taken with tiny forceps We won’t pretend it feels like nothing. It’s uncomfortable, mostly pressure and one stinging moment as the scope passes. Men often feel it more because the urethra is longer. It’s rarely painful, and slow breathing with relaxed pelvic muscles helps more than you’d expect. Recovery: What’s Normal and What Isn’t After the cystoscopy procedure, most people go home within an hour and are back at work the next day. After a biopsy or a rigid scope, plan on a few days of rest. For the first one or two days, these are normal: Burning or stinging when you pass urine Pink or lightly blood-tinged urine Needing to go more often than usual A mild ache in the lower belly What helps: A glass of water every hour or so while you’re awake on day one. It dilutes the urine and cuts the sting A warm compress on the lower belly, or a warm bath Paracetamol for discomfort. Skip aspirin-type painkillers unless we’ve okayed them No alcohol, heavy lifting or hard workouts for 24 to 48 hours Restarting blood thinners only when we tell you to Call us if you notice: Fever above 38°C or shivering Bright red urine with clots, or bleeding that doesn’t clear with water Trouble passing urine, or no urine at all Burning that gets worse after 48 hours Foul-smelling urine Serious problems are uncommon. A urinary infection or a little extra bleeding are the usual ones, and both respond well when treated early. Common Myths, Corrected “It means a hospital stay.” It doesn’t. A flexible check is a day-care visit, and you walk out the same day “Blood in the

Cystoscopy Explained: Why It’s Done and What Recovery Is Like Read More »

Urinary catheter with drainage tube and balloon, illustrating its uses, types and infection prevention, by Dr. Gaurav Aggarwal.

Urinary Catheter: When Is It Needed? 7 Proven Ways to Prevent Infection

Urinary Catheter: When Is It Needed? 7 Proven Ways to Prevent Infection Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  Say the word “catheter” in a clinic, and most people flinch. Fair enough. Nobody looks forward to a tube in the bladder. But in urology, a catheter is one of the most dependable tools we have. For a man who can’t pass urine or a patient waking up after cancer surgery, it keeps things safe while the body heals. The downside is infection. A urinary catheter gives bacteria a direct route into a part of the body that’s normally sterile, and the longer the tube stays, the easier that route gets. This guide covers when a catheter is truly needed, the main types, and the daily habits that lower your risk of catheter-associated urinary tract infection (CAUTI). What a Catheter Actually Does A urinary catheter is a thin, flexible tube that drains urine from the bladder into a collection bag. Most go in through the urethra. Some are placed through a small opening in the lower abdomen. Either way, the bladder is spared the job of emptying itself, which is exactly what you want when it can’t do that work alone. When Is a Catheter Needed? Doctors place one for a short list of clear reasons: Urinary retention: the bladder fills but won’t empty. An enlarged prostate, a narrowed urethra, a tumour blocking the bladder outlet or a nerve problem can all cause it. After surgery on the prostate, bladder or kidney: the tube keeps the bladder empty so fresh stitches and joins heal without pressure. After robotic prostate removal, it usually stays one to two weeks. After bladder removal with reconstruction, it can stay longer. Blood in the urine: clots can plug the outflow. A wider catheter lets us wash the bladder out and keep urine moving. Close fluid monitoring: after major operations or during critical illness, measuring urine hour by hour shows how the kidneys are coping. Pelvic tumours pressing on the urinary tract: a catheter gives relief while the treatment plan is sorted out. Severe incontinence when nothing else works: usually a last resort, used to protect the skin and keep a patient comfortable. Here’s the test I use. Is there a medical reason for this tube today? If the honest answer is “it’s easier for everyone”, the catheter should come out. Families can ask this question too, and they should. Main Types of Catheter Indwelling (Foley): sits inside the bladder, held in place by a small balloon filled with sterile water. Used for short or long stretches. Intermittent: passed, drained and removed several times a day. Infection risk is lower than with a tube that stays in, and many people with long-term retention learn to do it themselves. Suprapubic: placed through the lower abdomen straight into the bladder. Suits long-term needs or cases where the urethra can’t be used. External (condom) catheter: fits over the penis and collects urine outside the body. It works for men who can empty the bladder but can’t reach a toilet in time. It needs regular skin checks. Your doctor picks the right urinary catheter based on why you need it and for how long. Why CAUTI Happens  Normally, urine flushes bacteria out of the body every time you pass it. A catheter interrupts that. Germs creep up the outside of the tube from the skin and the urethral opening or get in through the drainage bag connection. Within days they can form a slimy film called biofilm on the tube surface, and antibiotics struggle to get through it. Catheter-associated urinary tract infection is one of the most common infections picked up during hospital care. Commonly cited estimates put the added risk at roughly 3 to 7 per cent for every day the tube stays in. A catheter removed on day two and one left for ten days are not the same risk. You’re more likely to run into trouble if you: Are older or have diabetes Have a weakened immune system, including during cancer treatment Are a woman, because the urethra is shorter Need the catheter for a long time Have kidney stones or other urinary blockages Struggle with bowel hygiene around the tube Signs of Infection Watch for these, especially in the first week: Fever or chills Pain low in the belly, in the back or along the side Burning, or a constant urge to pass urine Urine that smells strong or has blood in it Leaking around the tube New confusion or unusual drowsiness in an older person, which is sometimes the only clue One thing worth knowing: cloudy urine alone doesn’t mean infection. Bacteria can sit in the urine without causing any symptoms, and that usually doesn’t need antibiotics. Treat the patient, not the lab report. Antibiotics taken without need only breed resistant germs. How to Lower Your Risk Questions for your care team: Do I still need this catheter today? Ask every day, in hospital and at home. When is the removal date? Get it in writing if you can. Could intermittent or external drainage work instead? Was it inserted using sterile technique, and is it the smallest size that does the job? Do I need preventive antibiotics? Usually not. Routine ones don’t reduce infection and add resistance. Daily care at home: Wash your hands with soap and water before and after touching the tube or bag. Clean the skin where the tube enters once a day and after every bowel movement, wiping away from the tube. Skip powders and creams unless advised. Keep the bag below bladder level at all times, even while walking. Raising it lets urine flow back. Never let the bag rest on the floor. Empty the bag when it’s about two-thirds full, using a clean container, and don’t let the tap touch it. Leave the system closed. Don’t disconnect the tube from the bag unless you’ve been taught how. Secure the tube to your thigh or lower belly so

Urinary Catheter: When Is It Needed? 7 Proven Ways to Prevent Infection Read More »

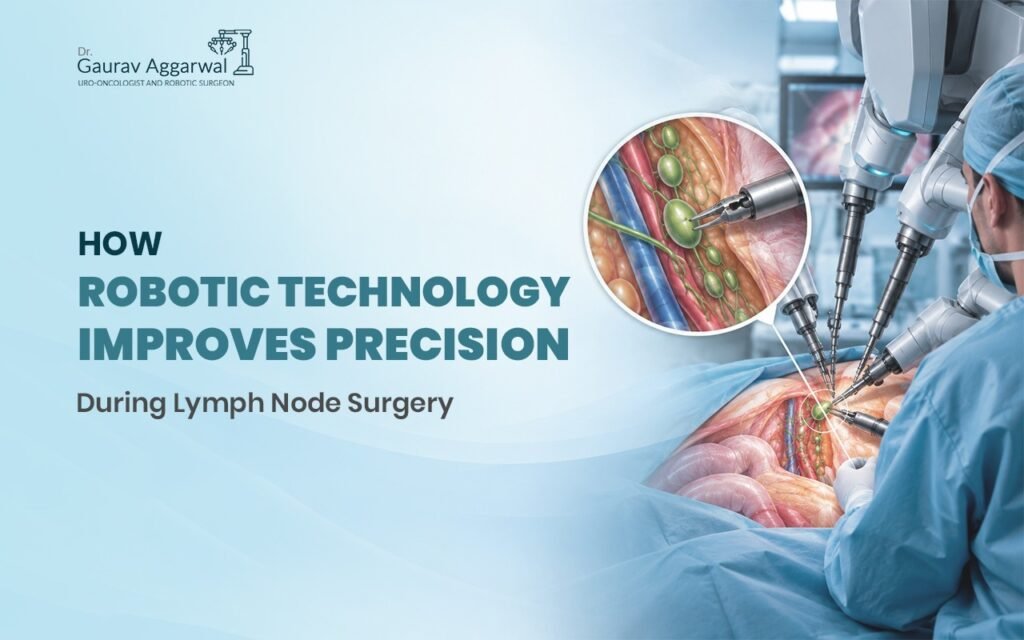
Illustration of robotic lymph node surgery highlighting surgical precision and advanced minimally invasive cancer treatment techniques.

How Robotic Technology Improves Precision During Lymph Node Surgery

How Robotic Technology Improves Precision During Lymph Node Surgery Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  When cancer spreads, it doesn’t travel randomly. It follows a predictable path through the lymphatic system. Surgeons have known this for decades. What changed in the last ten years is our ability to see and remove only the affected nodes—without collateral damage. Robotic technology during lymph node surgery has redrawn what’s possible. Instead of making large incisions to find and remove lymph nodes, surgeons now work through 4-5 tiny openings. The robot’s camera shows a magnified, three-dimensional view. The instruments move with precision that human hands alone cannot replicate. The result: fewer complications, faster recovery, and better cancer outcomes. This shift has been transformative for urological cancers. Prostate cancer, kidney cancer, and bladder cancer all rely on accurate lymph node assessment. Understanding whether cancer has spread to the nodes changes everything—from staging to prognosis to treatment decisions. Why Lymph Nodes Matter in Cancer Surgery The lymphatic system is the body’s early warning system. When a tumour grows, cancer cells often reach nearby lymph nodes first. If nodes are clear, the cancer is localised. If nodes are involved, the cancer has begun to spread. For urological cancers, this matters surgically: A surgeon needs to know which nodes are involved before operating Removing too many nodes causes long-term swelling (lymphoedema) Leaving involved nodes in place misses the cancer The nodes are deep—buried in fat and tissue, near vital blood vessels and organs Traditional open surgery required large incisions to access these areas safely. A surgeon could see, but only from one angle. Palpating tissue (feeling with gloved hands) helped identify nodes, but it wasn’t precise. Some nodes stayed behind. Others got removed unnecessarily. How Robotic Lymph Node Surgery Works Robotic technology doesn’t replace the surgeon. It extends the surgeon’s ability. The setup: Anaesthesia is induced, and the patient is positioned for access to the surgical area 4-5 small incisions (about 8-12 mm each) are made A camera (called an endoscope) goes through one port; instruments through the others The surgeon sits at a console 10 feet away, controlling the robot’s arms The precision advantage: The camera magnifies the area 10-12 times The image is three-dimensional, giving true depth perception The surgeon’s hand movements are scaled down—a 1cm hand movement becomes a 1-2mm instrument movement Tremor is filtered out automatically Articulated instruments bend and rotate in ways human wrists cannot What the surgeon sees: Individual lymph nodes sitting in their tissue beds Nearby blood vessels and nerves in high definition The exact plane between healthy tissue and cancerous tissue The ability to remove nodes without damaging structures nearby The Clinical Advantage Studies from urology centres across India and globally show consistent benefits: Better cancer staging: More nodes are identified and removed when indicated Staging accuracy improves, meaning treatment is based on complete information Understaging (missing nodes) drops significantly Reduced side effects: Lymphoedema rates fall because only necessary nodes are removed Infection risk is lower—smaller incisions mean less tissue trauma Nerve injury is less common because visualisation is superior Faster recovery: Patients go home 1-2 days after surgery instead of 3-5 days Return to normal activity happens in 2-3 weeks instead of 6-8 weeks Pain is minimal—small incisions mean minimal wound pain Better long-term outcomes: Cancer recurrence rates reflect improved staging and more complete node removal Quality of life improves because complications are fewer Lymph Node Surgery in Different Urological Cancers Prostate cancer: Robotic-assisted lymph node removal happens during prostatectomy Nodes in the pelvis are accessed safely through the same small incisions Precision matters because nearby nerves control sexual and urinary function Kidney cancer: Nodes around the kidney and in the retroperitoneum (behind the abdomen) are difficult to reach Robotic access allows removal without opening the belly fully The surgeon can work in a confined space without hand strain Bladder cancer: Pelvic lymph node removal is standard before removing the bladder The robotic approach is gentler on surrounding tissue Recovery is faster, which matters because bladder cancer patients often need follow-up chemotherapy Testicular cancer: Nodes in the retroperitoneum are deep and close to major blood vessels Robotic magnification reduces the risk of vascular injury Even small errors matter in this delicate region What to Expect: Before, During, and After Robotic Lymph Node Surgery Before surgery: Imaging (CT or MRI) identifies the location of nodes needing removal Blood work and cardiac clearance are standard You’ll meet the surgical team and anaesthesiologist Fasting instructions are given (usually 6 hours before surgery) During the procedure: Total time in the operating room is typically 2-4 hours depending on the extent of lymph node surgery You’re under general anaesthesia the entire time The robotic system is positioned, and small incisions are made Node removal takes place; tissue is sent to pathology Incisions are closed with dissolving stitches or clips After surgery: Recovery room monitoring for 1-2 hours Most patients go home the same day or the next morning Pain is managed with oral medication Activity restrictions are minimal—walking and light movement start immediately Shower restrictions apply to incisions until they’re sealed (usually 3-4 days) Follow-up is at 1-2 weeks, then 4-6 weeks Robotic Lymph Node Surgery: Key Advantages Magnified three-dimensional view eliminates guesswork Smaller incisions reduce pain, infection risk, and recovery time Precise node dissection means better staging and fewer side effects Nerve and blood vessel injury risk drops significantly Patients return to normal activity faster Cancer outcomes improve because staging is accurate Working With an Experienced Robotic Surgeon Not all surgeons perform robotic lymph node surgery. The learning curve is steep. A surgeon needs hundreds of cases—not dozens—before they handle complex node dissections confidently. Look for: Board certification in urology and specific robotic credentialing Documented experience with 1,000+ robotic procedures Specialisation in cancer surgery (uro-oncology) Access to current-generation robotic systems A team that follows your case before and after surgery Dr Gaurav Aggarwal, based in Newtown, Kolkata, specialises in uro-oncology with robotic precision. His experience spans over 1,500 robotic

How Robotic Technology Improves Precision During Lymph Node Surgery Read More »

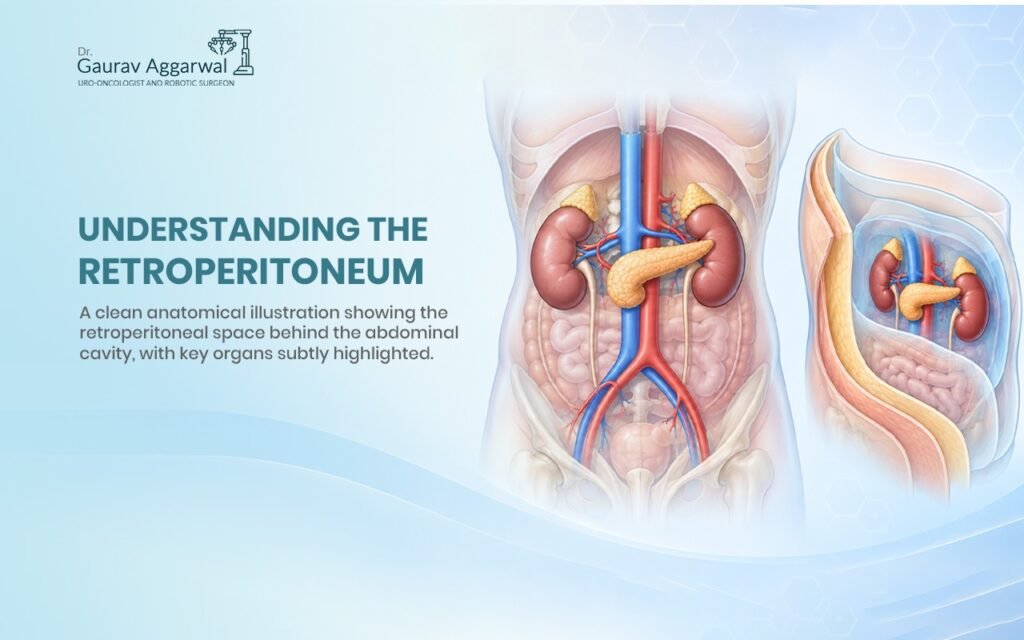
give me a img alt text based on focus keyword Retroperitoneum anatomy showing major organs, including kidneys, adrenal glands, ureters, and surrounding structures.

What Is the Retroperitoneum? Anatomy, Organs and Functions Explained

What Is the Retroperitoneum? Anatomy, Organs and Functions Explained Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  When patients come to see me with kidney problems, prostate issues, or urological conditions, I often need to explain where things are located inside their body. That’s when I start talking about the retroperitoneum. Most people have never heard of it, and honestly, that’s understandable. It’s not an organ you can point to or something you think about unless something goes wrong. But here’s the thing—understanding what is the retroperitoneum and why it matters has helped many of my patients grasp why their condition needs the treatment it does. So let me walk you through it. What Is the Retroperitoneum, Actually? The retroperitoneum is a space. Not an organ, not a tissue—a space. Specifically, it’s the area behind your abdominal cavity that sits between the peritoneum (a membrane lining your abdomen) and the back wall of your abdomen. Think of it this way: inside your belly, you have your intestines, stomach, liver, and other organs. These organs have a protective lining around them called the peritoneum. Everything inside that lining is called the peritoneal space. But behind that lining—behind the peritoneum—there’s another space. That’s the retroperitoneum. When I perform robotic surgery on the kidneys or prostate, I’m often working in this retroperitoneal space. This is where the important structures hide, which is why understanding the anatomy matters. What Organs Are in the Retroperitoneum? This is where it gets clinically interesting. Several vital organs live in this space, and they’re crucial to your body’s function.   The kidneys sit in the retroperitoneum on either side of your spine, one on the left and one on the right. These filter your blood and produce urine. As a urologist, the kidneys are central to what I treat.   The ureters run from your kidneys down to your bladder, carrying urine. They travel through the retroperitoneum the entire way.   The adrenal glands sit on top of each kidney. They produce hormones that regulate stress response, blood pressure, and metabolism. Major blood vessels pass through here too: The abdominal aorta (the largest artery in your body, carrying blood from your heart) The inferior vena cava (the large vein returning blood to your heart) Smaller arteries and veins branching to the organs   The pancreas sits in the retroperitoneum behind your stomach. It produces insulin and digestive enzymes. Parts of the duodenum and colon also sit retroperitoneally. These are parts of your digestive system. The psoas muscles run through the retroperitoneum along your spine, helping you flex your hip. Why Does This Matter? You might be thinking, “Okay, so these organs are back there. Why should I care where they are?” It matters because location determines treatment options. When I’m dealing with a kidney tumor or a prostate condition, the retroperitoneum means how I can access it, what structures I need to be careful around, and whether robotic surgery is the right approach.   In my practice, understanding the retroperitoneal anatomy is why we can perform minimally invasive procedures. When I use robotic surgery to remove a kidney, I’m working through the retroperitoneal space with precision. I can see the structures clearly, avoid damaging surrounding tissues, and preserve function better than with open surgery.   If you have kidney stones stuck in your ureter, they’re stuck in a retroperitoneal structure. If you have an infection in the retroperitoneum, it’s potentially serious because that space isn’t as easy to access and treat as other areas. How Does the Retroperitoneum Stay Protected? One reason retroperitoneal infections are dangerous is because this space isn’t as open as other parts of your abdomen. The organs and tissues here are enclosed by fascia—connective tissue that acts like a protective wrapper.   This fascia is called Gerota’s fascia around the kidney. It holds the kidney in place and helps contain any infection or bleeding. But it also means that if something goes wrong, it can be harder to detect and treat early because symptoms might not show up as quickly. Surgeons need to respect this anatomy. When I’m working in the retroperitoneum, I’m navigating around: Major blood vessels (you don’t want to accidentally cut the aorta) Nerve structures Existing inflammation or scarring The fascia layers This is why a surgeon’s understanding of retroperitoneal anatomy isn’t just academic—it’s essential for patient safety. Common Conditions Affecting the Retroperitoneum Over my years in practice, I’ve treated patients with various retroperitoneal conditions: Kidney stones get stuck in the ureter, which runs through the retroperitoneum. They cause intense pain and need to be removed or dissolved.   Renal cell carcinoma (kidney cancer) starts in the kidneys and may spread within the retroperitoneal space. Surgery to remove the kidney requires understanding exactly how far the cancer has spread. Retroperitoneal fibrosis is a rare condition where fibrous tissue builds up in the retroperitoneum, potentially trapping the ureters and blocking urine flow. This is serious and requires intervention. Aortic aneurysms affect the abdominal aorta, which runs through the retroperitoneum. This is life-threatening and requires urgent surgery.   Kidney infections can spread into the retroperitoneal space. Because it’s a confined space, this can become critical quickly.   Prostate conditions directly affect structures adjacent to the retroperitoneum, which is why understanding this anatomy helps with treatment planning. Retroperitoneal Surgery and Robotic Technology This is where my speciality gets interesting. When we need to surgically treat retroperitoneal conditions, we have choices. Traditional open surgery means making a large incision, opening the abdomen, and working with our hands. For some cases, this is still necessary. But robotic-assisted surgery has changed how I approach many retroperitoneal procedures. With the da Vinci robot, I have better visualization of the retroperitoneal space. The camera gives me high-definition, three-dimensional imaging. My instruments have more precision than my hands alone can achieve. This means smaller incisions, less tissue damage, faster recovery, and better outcomes for patients.   When I’m doing a robotic nephrectomy (kidney removal) for cancer, I can

What Is the Retroperitoneum? Anatomy, Organs and Functions Explained Read More »

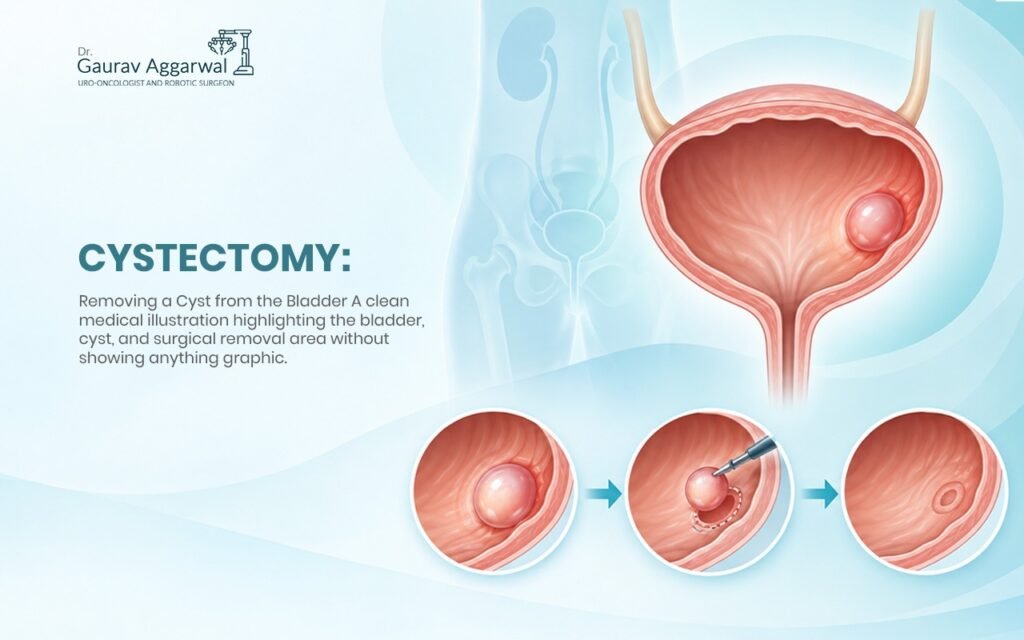
Bladder removal surgery (cystectomy) illustration showing the urinary bladder and surrounding organs.

What Is a Cystectomy, and When Is It Needed?

Bladder Removal Surgery (Cystectomy): When Is It Needed & Why? Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  Bladder removal surgery, medically known as cystectomy, is a surgical procedure involving the partial or complete removal of the urinary bladder. If you or someone you know has been told this surgery might be necessary, you probably have questions. What does it mean to lose your bladder? How does the body handle urination afterward? Is this really the best option? This guide walks through what a cystectomy actually involves, why doctors recommend it, and what to expect. For most people, the bladder is invisible—you simply use the bathroom when you need to. But when bladder cancer develops or certain conditions damage the bladder beyond repair, removal becomes the best path forward. What a cystectomy isn’t is a small procedure. It’s a major surgery that changes how your body functions. Understanding it means understanding both the surgery itself and the real reasons your doctor is recommending it. What Is Bladder Removal Surgery (Cystectomy)? What is a cystectomy in the simplest terms? It’s the surgical removal of the entire bladder. In men, this usually means removing the bladder, prostate, and seminal vesicles. In women, it means removing the bladder, uterus, ovaries, and part of the vagina. The surgeon doesn’t just take out the organ and leave nothing. They reconstruct a way for urine to leave the body. After a cystectomy, urine has nowhere to go in the traditional sense. The body needs a new path for waste. Surgeons create this through: A urostomy (ileal conduit) – using a small piece of intestine to create a new passage for urine to an opening in the abdomen A continent pouch – reshaping the intestine to create an internal reservoir that you empty through a catheter A neobladder – reconstructing a bladder-like pouch from the intestine so you can urinate more naturally, though typically you’ll need to catheterise The type of reconstruction depends on your age, health, cancer stage, and preference. Why Do Doctors Recommend Bladder Removal Surgery? The most common reason for cystectomy is bladder cancer, particularly muscle-invasive bladder cancer that has penetrated deep into the bladder wall. At this stage, removing the entire bladder gives the best chance of eliminating cancer completely. Radiation and chemotherapy might shrink tumours, but they don’t guarantee the cancer won’t return. A cystectomy removes the source. Cystectomy is also recommended for: Bladder cancer that has spread to the prostate (in men) or upper vagina (in women) Recurrent bladder cancer that keeps returning after other treatments Severe bladder damage from radiation therapy Neurogenic bladder that’s become untreatable and is causing serious infections Bladder rupture or trauma that can’t be repaired Chronic inflammation that has damaged the bladder beyond function For cancer specifically, the decision comes down to this: bladder cancer is treatable, but only if caught and treated aggressively. What a cystectomy represents is that aggressive treatment—removing the problem before it spreads further. How Is Bladder Removal Surgery Performed? This is major surgery requiring general anaesthesia and typically takes 3 to 5 hours. The surgeon makes an incision in the lower abdomen to access the bladder. They remove the bladder along with surrounding lymph nodes (to check for cancer spread). Then they create the new urinary system. Robotic surgery has changed how this procedure is performed. Instead of one large incision, the surgeon makes several small ones and works through a robotic system, which allows for greater precision. Robotic cystectomy reduces blood loss, shortens hospital stays, and speeds recovery compared to open surgery. During surgery, several things happen: The bladder is removed completely Nearby lymph nodes are taken and tested The urethra is carefully handled to preserve as much function as possible The new urinary pathway is created using intestinal tissue All connections are tested to ensure they work correctly Drains are placed to prevent fluid buildup The surgery is complex. Recovery takes weeks, not days. Recovery After Bladder Removal Surgery After cystectomy, you’ll spend 2 to 4 days in the hospital. Pain management is essential for the first few weeks. Most people need 4 to 6 weeks before returning to normal activities, though full recovery takes closer to 8 to 12 weeks. During recovery: You’ll have a catheter (tube) draining urine into a collection bag – this prevents pressure on the new system while it heals Drains remove fluid from the surgical site to prevent buildup Pain medication helps manage discomfort as you heal Diet progresses gradually from liquid to solid food You’ll need to learn how to manage your new urinary system Follow-up appointments monitor healing and teach you self-care The first few weeks feel heavy. You have tubes, pain, and limited mobility. But each week improves. By 4 to 6 weeks, most people feel substantially better. By 3 months, they’re back to their regular routines—just with a different way of managing urination. Adjusting to Life After Cystectomy The permanent change is learning to manage urine without a bladder. If you have an ileal conduit (the most common reconstruction), you’ll wear a pouch on your abdomen that collects urine throughout the day. You empty it when needed—typically 4 to 6 times daily. It becomes routine, like any other daily task. With a continent pouch, you catheterise yourself through an opening in the abdomen 4 to 5 times daily. With a neobladder, you urinate more normally but may need catheterisation occasionally. The adjustment period is real. People report: Learning to manage the pouch or catheterisation effectively Adjusting to the physical sensation of something new on their body Regaining confidence in their routine and social activities Returning to work, exercise, and hobbies Adapting intimate relationships as they figure out what feels comfortable Managing occasional leakage and how to handle it discreetly Most people adapt within 2 to 3 months. The key is patience with yourself during that learning period. Why This Surgery Saves Lives For muscle-invasive bladder cancer, cystectomy offers the best survival outcomes. Patients who undergo cystectomy have higher

What Is a Cystectomy, and When Is It Needed? Read More »

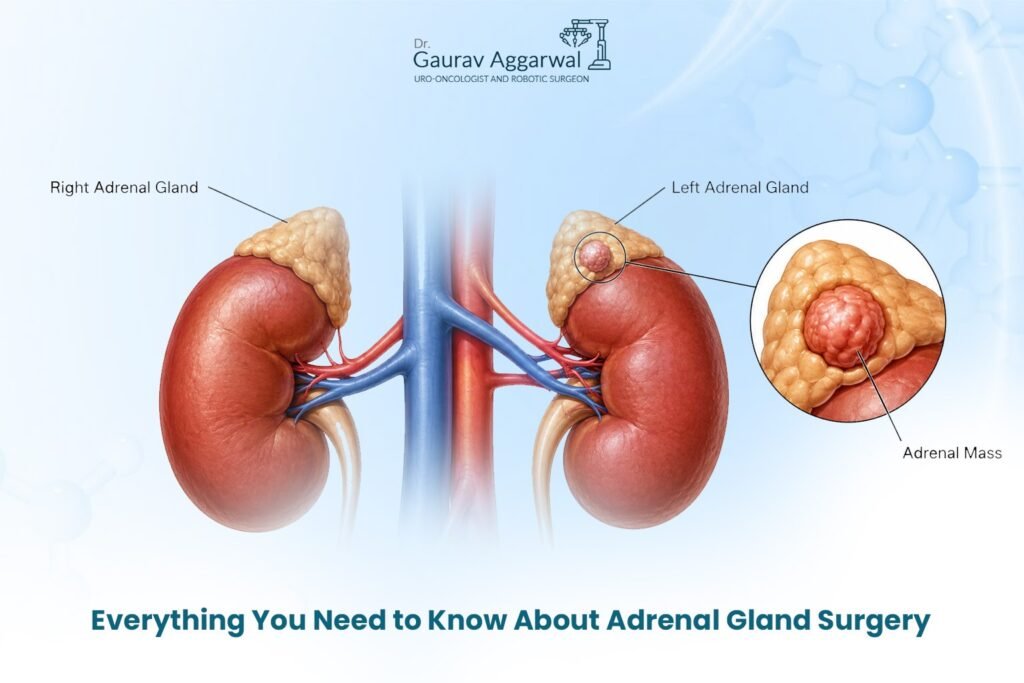
adrenal cancer treatment in Newtown

Everything You Need to Know About Adrenal Gland Surgery

Everything You Need to Know About Adrenal Gland Surgery Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  Adrenal gland surgery can sound intimidating, especially when it is being discussed as part of cancer treatment. Understanding what the surgery involves and what recovery looks like can make the process more manageable. The adrenal glands are small hormone-producing organs located above the kidneys, but they have an important role in regulating blood pressure, metabolism, and the body’s response to stress. Adrenal cancer is rare, and treatment needs to be planned carefully based on the size and location of the tumour, whether it produces hormones, whether it has spread, and the patient’s overall health. For patients exploring adrenal cancer treatment in Newtown, surgery is often the main curative option when the disease is localised. Understanding Adrenal Gland Cancer Adrenal cancer, also known as adrenocortical carcinoma (ACC), develops from malignant cells in the adrenal cortex. It accounts for approximately 0.05-0.2% of all cancer diagnoses, making it an uncommon condition that requires specialised evaluation and surgical expertise. Not every adrenal tumour behaves in the same way. Some tumours are functional, meaning they produce excessive hormones, while others are non-functional and may not cause hormone-related symptoms. Important factors doctors consider include: Tumour size and growth Whether the tumour has invaded nearby tissues Lymph node involvement Spread to distant organs Hormone production The patient’s age and overall health Possible inherited cancer syndromes Because adrenal tumours can sometimes resemble benign growths, diagnosis usually involves a combination of hormonal testing and detailed imaging. In selected cases, a biopsy may also be considered. What Symptoms Can Adrenal Cancer Cause? Adrenal cancer can present differently from one person to another. Some patients experience hormone-related symptoms, while others may have more general symptoms or discover the tumour accidentally during imaging for another health concern. Hormone-related symptoms can include: High blood pressure and low potassium levels Changes caused by excess cortisol Virilization or feminization due to abnormal sex hormone production Central weight gain, muscle weakness, skin striae, or glucose intolerance Mood or psychiatric changes associated with hormonal excess Other possible symptoms include: Abdominal or flank pain A palpable abdominal mass in larger tumours Fatigue Unexplained weight loss Loss of appetite Sometimes, adrenal cancer is found incidentally during a scan performed for an unrelated reason. How Is Adrenal Cancer Diagnosed? A detailed diagnostic assessment helps the medical team understand exactly what they are dealing with before surgery is planned. The evaluation may include: Hormonal assessment, including 24-hour urine cortisol, plasma ACTH, aldosterone-renin ratio, and androgen levels CT scans using a fine-cut protocol MRI to assess tumour size, characteristics, invasion, and possible spread Biopsy when imaging does not provide a clear diagnosis Chest and abdominal imaging, and sometimes PET-CT, for staging Genetic evaluation in selected patients with a possible hereditary risk This information helps the team plan surgery with the goal of complete tumour removal while protecting surrounding structures. Surgical Approaches to Adrenal Cancer Treatment in Newtown For localised adrenal cancer, adrenalectomy, or surgical removal of the affected adrenal gland, is generally the primary curative approach. The aim is complete tumour removal with negative surgical margins. Depending on the tumour and the patient’s condition, the surgeon may recommend one of several approaches. Robotic-Assisted Adrenalectomy Robotic surgery has become an important option in selected adrenal cases. It uses a high-definition camera and specialised instruments that allow the surgeon to work with enhanced visualisation and precision. Potential advantages can include: Magnified visualization of delicate adrenal structures Greater instrument stability and tremor filtering Small port incisions and reduced surgical trauma Less postoperative pain in suitable cases Faster recovery and shorter hospital stays Better access in anatomically complex situations Robotic techniques may help in complex cases, but tumour characteristics and oncological safety remain the priority. Open Adrenalectomy An open approach provides broad access to the tumour and surrounding anatomy. It may be recommended when a tumour is very large, involves major blood vessels, or cannot be safely removed using minimally invasive techniques. Open surgery can also allow en bloc removal of nearby organs if the tumour has invaded them and complete cancer removal requires it. The trade-off is generally a longer hospital stay and recovery period. Laparoscopic Adrenalectomy Laparoscopic surgery uses small incisions and specialised instruments. It can reduce surgical trauma and support quicker recovery in appropriately selected patients. However, it is generally more suitable for smaller tumours without extensive vascular involvement, and the technical demands can be significant. The final surgical decision depends on the tumour, the patient’s physiology, the extent of disease, and the surgeon’s expertise. In cancer surgery, achieving safe and complete tumour removal is more important than choosing a particular technology. Preparing for Surgery Good preparation is especially important when the tumour produces hormones. Before surgery, the medical team may focus on: Controlling excess hormone production Correcting low potassium levels Assessing blood pressure and other metabolic changes Planning specialized anesthesia Reviewing imaging to understand blood vessels and nearby organs Planning lymph node management when clinically indicated During surgery, careful haemodynamic monitoring is important because manipulating a hormone-producing tumour can sometimes trigger sudden hormone release. Meticulous dissection also helps reduce the risk of tumour spillage and injury to surrounding structures. Adrenal surgery is often a multidisciplinary process involving urologists, oncologists, anaesthesiologists, radiologists, and pathologists. This coordinated approach helps ensure that diagnosis, surgery, and postoperative care work together rather than functioning as separate steps. Recovery After Adrenal Surgery Recovery after adrenal cancer treatment in Newtown depends on the surgical approach, tumour characteristics, and the individual’s overall condition. For minimally invasive procedures, the hospital stay is typically around 1-3 days, while open surgery may require approximately 3-5 days. Pain is usually managed using a multimodal approach, with the aim of providing effective relief while limiting unnecessary opioid use. Patients are generally encouraged to gradually increase activity. A return to normal activities may take around 4-6 weeks, while strenuous activity is restricted initially to allow proper healing. Hormone replacement depends on how much adrenal tissue remains. After

Everything You Need to Know About Adrenal Gland Surgery Read More »

Uro-Oncologist in Newtown Kolkata

Why Regular Health Check-Ups Can Help Detect Urological Diseases Early

Why Regular Health Check-Ups Can Help Detect Urological Diseases Early Authored by: Dr Gaurav Aggarwal (Uro-oncologist and Robotic Surgeon)  When it comes to your health, waiting for something to feel wrong is not always the best approach. Some urological diseases, including cancers, can develop quietly without causing noticeable symptoms in the early stages. By the time warning signs appear, the condition may already have progressed. That is why regular health check-ups matter. They give you and your doctor an opportunity to identify potential problems earlier, understand your individual risk, and decide on the right course of action. Early detection can make treatment simpler, improve outcomes, and help protect your quality of life. Why Early Detection Matters in Urological Cancers Many urological cancers can develop silently. A person may feel completely fine while changes are already taking place inside the body. Regular screening can help identify these changes before they become more difficult to treat. Early detection can offer several important advantages: Symptom-free detection: Cancer may be identified before noticeable symptoms appear. Smaller tumour size: Early-stage tumours are generally smaller and more contained. Better treatment outcomes: localised disease often responds more favourably to treatment. More treatment choices: Early detection can make minimally invasive approaches, including robotic surgery, possible. Improved survival rates: Detecting cancer early can significantly improve long-term outcomes. Better quality of life: Early treatment can mean fewer complications and a faster recovery. Simply put, waiting for symptoms is not always the safest strategy. Understanding Prostate Cancer Screening Prostate cancer is the most common urological cancer among men. Regular screening helps doctors understand what is happening with the prostate and whether further investigation may be needed. Depending on your age and individual risk, screening may include the following: PSA blood test: Measures prostate-specific antigen levels. An elevated result may require further evaluation. Digital rectal examination (DRE): Helps assess the size and texture of the prostate. Risk assessment: Screening results help determine whether additional imaging or a biopsy may be appropriate. Baseline testing: An initial result provides a reference point for future comparisons. Age and family history: Men with a family history may need to begin screening earlier. Personalised monitoring: Your urologist can recommend the appropriate screening frequency based on your individual risk. Not every man needs the same screening schedule. Your doctor should personalise the approach according to your health profile and risk factors. Who Should Consider Regular Screening? While everyone can benefit from paying attention to their urological health, certain groups may need closer monitoring. Regular check-ups are particularly important for: Men over 50: Age is an important risk factor for prostate cancer. Men with a family history: A family history can increase cancer risk. Men over 40 with a family history: Earlier screening may be recommended for higher-risk families. African men: Higher incidence rates make proactive monitoring particularly important. Men with elevated PSA: Previous abnormal results may require continued surveillance. Men experiencing symptoms: Urinary or pelvic symptoms should be evaluated promptly. Regular monitoring can act as an early warning system, especially for people who are more likely to develop urological diseases. The Role of Advanced Imaging in Early Detection Modern diagnostic technology has made it possible for doctors to investigate suspicious findings with greater accuracy. Depending on the situation, your doctor may recommend advanced diagnostic tests such as: MRI fusion imaging: Helps with precise tumor localization. Transrectal ultrasound: Can guide biopsy procedures. CT scanning: Helps determine whether cancer has spread beyond the prostate. PET imaging: Can help identify metastatic disease in advanced cases. Biomarker testing: May provide information about cancer aggressiveness and progression risk. Genomic testing: Can help predict treatment response and individual prognosis. These technologies give doctors a clearer picture of the disease and help them make more informed treatment decisions. Why Robotic Expertise Matters in Prostate Cancer Treatment When prostate cancer is detected at an early stage, choosing the right treatment team becomes an important part of the journey. The best robotic surgeons for prostate cancer can offer patients access to highly precise, minimally invasive surgical treatment when robotic surgery is appropriate. Robotic surgery can provide the following: Precision and control: Robotic systems allow highly precise surgical movements. Nerve preservation: Enhanced visualisation can help surgeons protect important nerves. Minimal invasion: Smaller incisions can reduce surgical trauma and blood loss. Faster recovery: Patients can often return to normal activities sooner. Better functional outcomes: Early-stage treatment may help preserve continence and sexual function. Cancer control: Robotic prostatectomy can provide effective oncological treatment. Early detection combined with experienced robotic surgical care can create a more favourable treatment pathway for eligible patients. Symptoms You Should Never Ignore Although some urological cancers may have no symptoms in their early stages, certain changes should never simply be brushed aside. Speak to a doctor if you notice: A weak urinary stream or difficulty emptying your bladder Sudden or increasing urinary urgency or frequency Pelvic, perineal, lower abdominal, or lower back pain Blood in the urine, whether visible or detected through testing Sudden changes in erectile function A lump or swelling in the testicle These symptoms do not automatically mean cancer. However, they deserve proper medical evaluation rather than being ignored. From Screening to Treatment: What Happens Next? One of the biggest concerns patients have after an abnormal screening result is, “What happens now?” The process generally follows a structured pathway: Initial screening: PSA testing, DRE, and risk assessment. Confirmation testing: MRI or other advanced imaging when required. Biopsy: Tissue sampling may be performed if indicated. Staging: Imaging helps determine whether the cancer is localised or has spread. Treatment planning: Your surgeon reviews the findings and discusses suitable treatment options. Intervention: Early-stage cancers identified through screening may proceed to robotic surgery. Having a clear pathway can make an otherwise stressful experience feel more manageable. What Can Happen When Detection Is Delayed? It is easy to postpone a health check when you feel perfectly fine. But delaying screening or ignoring symptoms can have consequences. Late detection may lead to the following: More advanced disease at

Why Regular Health Check-Ups Can Help Detect Urological Diseases Early Read More »